From Sample to Insight: The Clinical Laboratory Chain of Responsibility | Webinar

Safeguarding Samples, Data, and Decisions Across the Clinical Biomarker Journey

Overview

A clinical laboratory does far more than process samples and report results.

Every patient-derived sample passes through a chain of interconnected processes before it becomes interpretable biomarker data. Sample collection and handling, traceability, laboratory operations, analytical performance, data interpretation, and final delivery can all influence whether a biomarker result ultimately provides meaningful information for a clinical study.

Watch the replay of this Nordic Bioscience webinar, where we look beyond individual assays and laboratory technologies to examine the broader systems required to generate reliable, actionable biomarker insights.

Using the Chain of Responsibility as a framework, the webinar follows the clinical sample journey from collection through laboratory processing and biomarker measurement to data interpretation and its potential impact on clinical development.

The discussion examines where risks can arise, how laboratories work to protect sample and data integrity, and why reliable biomarker measurement depends on much more than analytical performance alone.

What you can expect to learn

  • Why the clinical laboratory’s responsibility extends beyond sample processing and biomarker measurement.
  • How pre-analytical factors can influence the quality and interpretability of biomarker data before a sample reaches the analytical stage.
  • Why accessioning, traceability, and controlled sample handling are essential throughout the clinical sample journey.
  • How operational and analytical excellence work together to generate reliable biomarker measurements at scale.
  • Why data interpretation and delivery are integral parts of the laboratory process rather than simply its final output.
  • How clinically meaningful biomarkers connect laboratory measurements with questions relevant to clinical development and patient outcomes.
  • Where risks can emerge across the sample journey and how an integrated laboratory framework can help reduce them.

Topics

1. Welcome and introduction

Prof. Dr. Morten Karsdal, CEO, Nordic Bioscience

An introduction to Nordic Bioscience, the speakers, and the central question of the webinar: what does it take to turn a patient-derived sample into biomarker data that can reliably support clinical research and decision-making?

2. The Chain of Responsibility: Five clinical laboratory processes essential for success

Charlotte Van Liedekerke, Senior Alliance Project Manager, Nordic Bioscience

The journey of a clinical sample does not begin when an assay is run, nor does it end when a result is generated.

This presentation introduces the Chain of Responsibility framework, following patient-derived samples through five interconnected areas that contribute to reliable and interpretable biomarker data:

  • Pre-analytical integrity – protecting sample quality from collection onwards.
  • Accessioning and traceability – maintaining control and visibility throughout the sample journey.
  • Operational and analytical excellence – ensuring robust, reproducible, and scalable laboratory execution.
  • Data interpretation and delivery – transforming analytical output into information that can be understood and used.
  • Clinically meaningful biomarkers – ensuring that what is measured can address relevant biological and clinical questions.

The presentation will explore risks across these stages and demonstrate why the reliability of biomarker data depends on the integrity of the entire process rather than any single analytical step.

3. Scientific perspective: Connecting laboratory quality with clinical development

Dr. Asger Reinstrup Bihlet, CSO, NBCD

A broader scientific and clinical-development perspective on why biomarker data must be considered in the context in which it is generated and ultimately applied.

The discussion will connect laboratory processes with the requirements of clinical studies and examine how robust sample management, biomarker strategy, and interpretation contribute to generating data that can support meaningful development decisions.

4. Q&A and discussion

All speakers

Open discussion and audience questions on the clinical sample journey, laboratory processes, biomarker implementation, and the challenges involved in generating reliable and decision-ready biomarker data.

Speakers

Prof. Dr. Morten Karsdal

  • Dr. Morten Karsdal joined Nordic Bioscience in 2001 and became CEO in June 2010, leading the company to significant advancements in biomarker development and disease biology.
  • Dr. Karsdal is a KOL in extracellular matrix research, with more than 700 publication, 44,684 citations, and an impressive H-index of 106.
  • Dr. Karsdal is an honorary professor of inflammation research at the University of Southern Denmark, where he continues to supervise PhD students, fostering the next generation of researchers.
  • Dr. Karsdal chairs the Extracellular Matrix Pharmacology Congress, an important forum for advancing drug development by focusing on the extracellular matrix (ECM) as a key factor in most chronic diseases. He is renowned for his deep expertise in fibrosis, rheumatology (including rheumatoid arthritis and osteoarthritis), diabetes, and other chronic conditions, particularly in relation to ECM and biomarker research.
  • Dr. Karsdal has led the development of FDA-approved and supported molecular diagnostics, as well as more than 100 commercialized biomarker assays, including ELISA assays and high precision automated platforms.
  • He has extensive experience in clinical trial design and the clinical application of biochemical markers, often serving as a consultant to major pharmaceutical companies for the use of serological biomarkers in clinical trials.
  • In 2016, he and his research team authored the first edition of “Biochemistry of Collagens, Laminins and Elastin,” published by Elsevier Science. The book, now in its 3rd edition as of 2023, is a key resource on collagens and structural proteins, with a focus on their applications in chronic diseases.

Charlotte Van Liedekerke

  • Charlotte Van Liedekerke is Senior Alliance Project Manager at Nordic Bioscience, where she works at the intersection of biomarker science, clinical research, and strategic pharmaceutical partnerships.
  • With a background in Biomedical Sciences from the KU Leuven and an MBA in Bio-Entrepreneurship from the Copenhagen Business School, she combines scientific expertise with business and project leadership.  
  • She partners with global pharmaceutical and biotechnology companies to manage biomarker projects, facilitating collaboration between clinical teams, laboratories, and key stakeholders throughout drug development programs. 
  • Prior to joining Nordic Bioscience, she conducted oncology research in Belgium, Austria, and Spain, providing her with hands-on experience across different research environments.  
  • Recognized on the Forbes Belgium 30 Under 30 list in 2024, she represents a new generation of professionals shaping the future of life sciences through collaboration between science and industry. 

Dr. Asger Reinstrup Bihlet

  • Dr. Reinstrup Bihlet is the Chief Scientific Officer of Sanos and is an internationally renowned expert in musculoskeletal drug development, pain, and clinical trial design.
  • He holds a PhD for the University of Southern Denmark, and a master’s in Pharmaceutical Science (M.Sc. Pharm) from University of Copenhagen.
  • During his 20+ years in the industry he has held several leading positions in pharma and clinical research organizations within regulatory affairs, medical affairs, and clinical science.
  • Dr. Reinstrup Bihlet has a H-factor of 22, and has published more than 50 peer-reviewed papers, primarily on musculoskeletal clinical science, in high-ranking journals including The Lancet and JAMA.
  • He is a frequent speaker at international MSK Conferences such as OARSI, EULAR, and ACR, where more than 100 original abstracts have been presented, in addition to invited speaker sessions on musculoskeletal trial design and placebo response mitigation.
  • As Chief Scientific Officer, he currently leads the scientific and medical activities of Sanos and the subsidiaries CROs including the leading Global MSK niche-CRO NBCD.
  • As chief scientist, has led of a long series of global trials totaling approximately 18,000 study participants evaluating experimental treatments in MSK conditions.
  • Dr. Reinstrup Bihlet is actively researching in the fields of arthritis and osteoporosis, with a particular focus on optimizing clinical trial methodology and outcomes.

The webinar was organized exclusively by Nordic Bioscience.
Most biomarker candidates die in the valley of death. What made PRO-C3 different?

Biomarker discovery has accelerated dramatically, but clinically viable products rarely follow. Thousands of protein signals are associated with disease every year, yet, relatively few become reliable tools for clinical development or patient management. Many stall in the biomarker valley of death: the long and resource-intensive space between initial discovery and validated clinical utility.

High-throughput omics and proteomics can identify thousands of disease-associated signals. But an association alone does not make a measurement an actionable biomarker. Biological specificity, analytical performance, clinical evidence and a clearly defined Context of Use must follow.

A new expert opinion in the Journal of Hepatology (IF 40 as of August 2026) proposes a higher standard. While the paper takes the liver field as an example, it’s findings are applicable to most diseases. It introduces the concept of the unicorn biomarker: a rare biomarker with diagnostic, prognostic and pharmacodynamic utility, supported by rigorous technical, clinical and regulatory development. PRO-C3, invented by Nordic Bioscience, is highlighted as one of the potential unicorn biomarkers approaching this standard. 

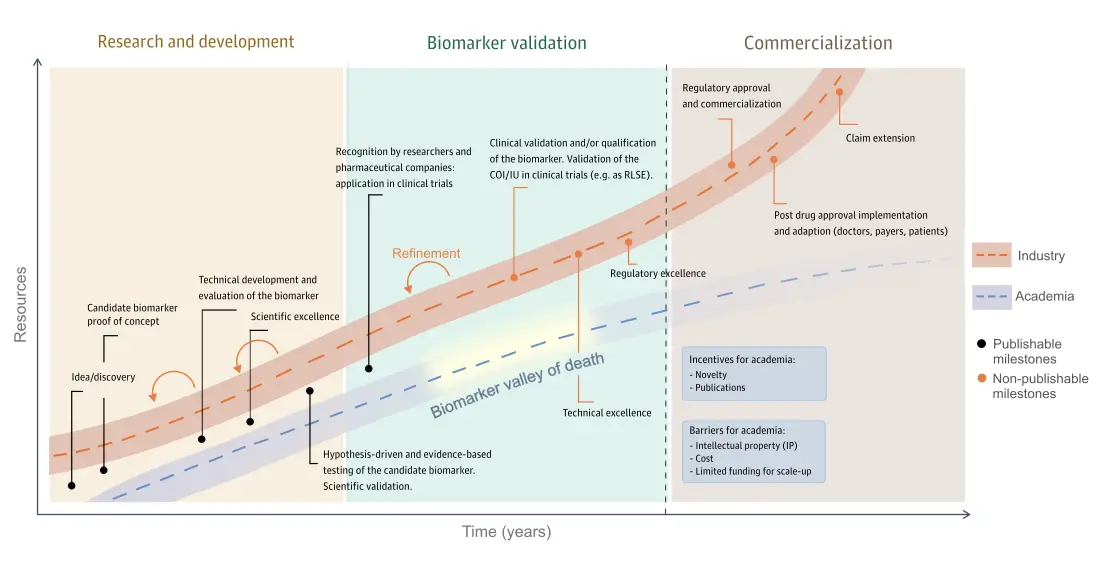
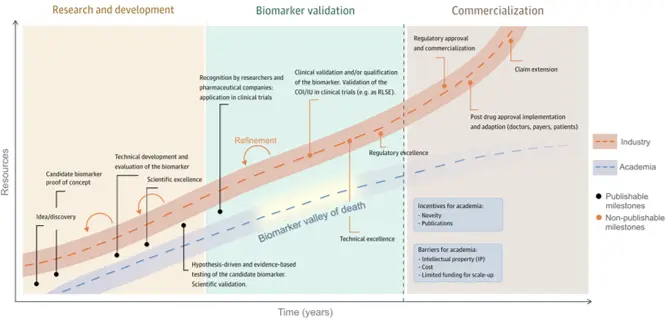
Most candidates die in the biomarker valley of death

Fig.1 The path to becoming a unicorn biomarker consisting of three stages: Research and development, biomarker validation, and commercialization.

Discovering a promising protein signal is only the beginning. To progress toward clinical utility, a candidate must undergo technical development, scientific and clinical validation, regulatory alignment and, ultimately, implementation on a reliable and scalable platform. Many candidates never progress beyond discovery or early validation, while others stall when the cost and technical requirements increase.

The journey begins with research and development, where a biomarker is discovered through scientific hypothesis testing. Most biomarkers remain in research and development, as advancing further requires investment in technical excellence and quality control. The second stage is the biomarker validation stage where biomarkers are validated in clinical trials and technical performance on the final assay design is rigorously tested. This phase is often called the “biomarker valley of death” because the work is costly, technically demanding, and rarely publishable, causing many candidates to stall.

The final stage is commercialization, which focuses on achieving regulatory approval for specific contexts of use (CoUs) or intended uses (IUs) and implementing marketing strategies to generate a return on the investment. Here, academia and industry collaborate to validate, adopt, market, and implement the biomarker for clinical applications.

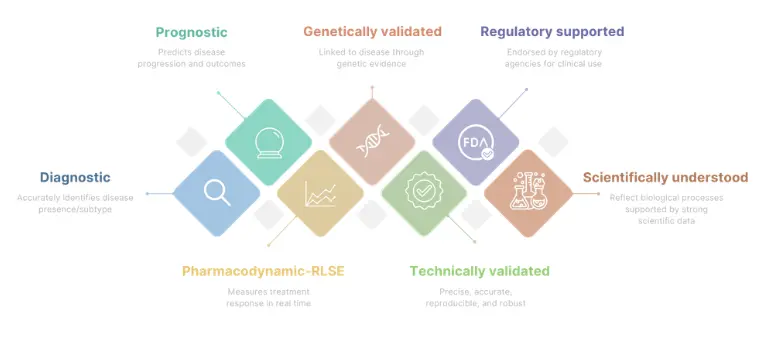
What does it take to become Unicorn biomarker?

Fig. 2 An outline of the requirements a unicorn biomarker has to fulfill.

Unicorn biomarkers are rare and valuable, as they must fulfill various requirements (Fig. 3). Unlike biomarkers that serve a single purpose, they provide value across multiple stages of research and clinical development. They combine diagnostic utility, prognostic utility and pharmacodynamic utility, which is a combination of requirements that can be challenging because the criteria often is conflicting. While diagnostic and prognostic biomarkers must reliably reflect stable disease characteristics, pharmacodynamic biomarkers need to be sufficiently sensitive and dynamic to detect treatment-induced changes.

Beyond clinical utility, a unicorn biomarker must also be scientifically understood, technically validated to ensure reliable and reproducible results, and regulatory supported to enable its use in clinical development and, ultimately, patient care. Only when these scientific, technical, clinical, and regulatory criteria come together can a biomarker be considered a true unicorn biomarker.

Why the exact protein measurement matters

Proteins exist in different fragments, modified forms, or structural regions, each reflecting different biological processes. As a result, two measurements of the same protein may not necessarily provide the same clinical or biological insight if they target different parts of the molecule.

This is why the exact molecular target matters in biomarker development. The value of a biomarker does not only depend on identifying the right protein, but on measuring the right part of that protein in the right biological and clinical context.

Fig. 3 The structural complexity of proteins and implications for quantification.

This is the principle behind our Nordic ProteinFingerPrint Technology™. By targeting specific protein fragments generated during extracellular matrix remodeling, the technology is designed to measure defined biological processes rather than total protein abundance alone. This enables a more precise understanding of whether tissue is being formed, degraded, or modified by disease-related enzyme activity, helping researchers connect biomarker measurements to disease mechanisms, progression, and treatment response.

PRO-C3: Journey toward Unicorn Biomarker Status

One example approaching this standard is nordicPRO-C3™. PRO-C3 detects a defined neo-epitope generated during type III collagen formation, linking the measurement to active fibrogenesis rather than total collagen abundance.

Its development has extended well beyond initial discovery. PRO-C3 has demonstrated diagnostic utility as part of the ADAPT score, prognostic value in fibrotic disease and pharmacodynamic utility for measuring treatment-related changes in fibrosis activity. It has also been used extensively in pharmaceutical clinical development.

The launch of Elecsys PRO-C3 by Roche Diagnostics transferred the measurement onto the globally established cobas platform as an IVD-labelled assay. This progression from a biologically defined neo-epitope to a clinically studied and commercially deployed assay is why the paper identifies PRO-C3 as a potential unicorn bomarker.

Why this matters for drug developers

Unicorn biomarkers are valuable to drug developers because they link biological mechanisms with measurable treatment effects. When associated to a clear Context of Use, they can support patient enrichment by identifying individuals with relevant disease activity, disease stage, or risk of progression. This can reduce heterogeneity in trials and improve the ability to detect a meaningful treatment effect.

Their pharmacodynamic utility is especially relevant to drug developers, as they can provide earlier evidence that a therapy is affecting the intended biological pathway before traditional clinical outcomes become visible. This can support proof-of-mechanism, dose selection, treatment monitoring, and go/no-go decisions, helping developers make more informed choices before moving into larger and more costly studies. By providing earlier and more mechanistic grounded information, they can reduce uncertainty, improve trial design, and help lower the risk of late-stage failure.

By combining diagnostic, prognostic, and pharmacodynamic utility with strong scientific, technical, and clinical validation, unicorn biomarkers represent an aspirational standard for biomarker development.

PRO-C3 is not an isolated discovery. It represents Nordic Biosciennce’s approach to biomarker development: begin with biologically meaningful protein fragments and continue through the technical, clinical and regulatory work required to make the measurement useful. We build biomarkers to cross the biomarker valley of death.

Myths and misconceptions about biomarkers

  • While some biomarkers may be subject to biological variability, many others such as NT-proBNP for heart failure or prostate-specific antigen (PSA) for prostate cancer have well-characterized reference ranges and robust assay reproducibility. In fact, standardization and quality control measures have significantly improved the reliability of many biomarker assays.

  • Although oncology has led the way, biomarkers are now well-established in many fields, including cardiology (e.g., troponin for myocardial infarction), hepatology (e.g., ELF or FIB-4 for liver fibrosis) [67], diabetes (HbA1c) and rheumatology (e.g., anti-CCP for rheumatoid arthritis). Their utility spans diagnosis, prognosis, and treatment monitoring across multiple disease domains.

  • While regulatory-grade validation is ideal for clinical implementation (particularly for RLSE or VSE CoUs), exploratory biomarkers can and should be incorporated into early-phase trials to guide hypothesis generation and decision-making and generating data that will enable eventual clinical validation for regulatory use later. Waiting for full validation can delay insights into their potential link to drug MoA or clinical efficacy and hinder development [81]. Further, the use of a biomarker during pre-clinical phases of drug development increases the likelihood of final regulatory approval from 8% to 25%.

  • Although biomarker assays introduce additional costs, these are often small compared with the overall expense of clinical trials. Biomarkers can support clinical development by providing mechanistic insights into treatment response and disease biology, thereby informing critical decisions related to efficacy, safety, and proof of mechanism. As a result, biomarkers may contribute to more efficient and informative clinical trials.
  • When biomarkers have a defined CoU, including their role, target population, and setting, they streamline rather than complicate regulatory pathways. In fact, the FDA’s BEST Resource provides a structured framework for qualifying biomarkers.

Discuss your biomarker strategy

Explore how biologically specific biomarkers could support patient enrichment, proof of mechanism, treatment monitoring or development decisions in your clinical program.

    Fibroblast Activity and Tissue Destruction in Autoimmune Disease | Webinar

    Fibroblast Activity and Tissue Destruction in Autoimmune Disease: Understanding Tissue Activity and Its Implications for Drug Development

    Overview

    The body continuously regenerates, which inherently means that tissue is constantly being broken down and formed. In autoimmune diseases we usually focus on inflammation and immune activity, but inflammation is what starts the process, not what causes the lasting harm. The damage comes when that balance tips, fibroblasts become activated, and cartilage, bone, and connective tissue are broken down faster than the body can repair them. 

    Watch the replay of this webinar to learn more about how evaluating tissue activity reveals what is actively happening in the disease biology, whether a treatment is truly working, and how these insights can support the development of better therapies in autoimmunity, PsA, RA, SSc and lupus. 

    Agenda

    • Introduction and welcome & Myth busting with Unicorn biomarkers | Prof. Dr. Morten Karsdal
    • When inflammation isn’t enough: Synovial Tissue Fibrosis as a Driver of Treatment-Refractory RA | Dr. Kevin Wei
    • From tissue biology to clinical application: how fibrogenesis and tissue destruction markers are used for prognosis, pharmacodynamics and prediction in RA, PsA and SSc | Dr. Anne-Christine Bay-Jensen
    • Fibrosis and inflammation of the Skin and Lung in Systemic Sclerosis: Tracking tissue remodeling, progression and treatment response with biomarkers | Prof. Dr. Shervin Assassi
    • Q&A

    Scientific topics

    Autoimmune diseases are commonly viewed through the lens of inflammation and immune activity. However, inflammation represents only part of the underlying disease biology. Fibroblast activation, extracellular matrix remodeling, and ongoing tissue destruction can provide complementary information about what is happening within affected tissues and how disease activity changes during treatment. 

    In psoriatic arthritis, tissue turnover biomarkers offer a way to investigate structural and connective tissue activity alongside traditional measures of inflammation. Understanding these processes may help distinguish different aspects of disease activity, monitor the biological effects of treatment, and provide additional insight into therapeutic response. 

    Rheumatoid arthritis is likewise characterized by substantial heterogeneity within the synovium. Distinct synovial pathotypes, including fibroblast-rich or fibroid phenotypes, point to disease mechanisms that may not be adequately described by inflammatory activity alone. Emerging research into fibroblast states, synovial organization, and the regulation of fibrogenesis is therefore changing how we understand persistent disease and differences in treatment response. 

    Across systemic sclerosis, lupus, and autoimmunity more broadly, the same principle applies. Many different disease pathways end up driving the same core process: the breakdown and rebuilding of tissue. This means disease activity can be understood as the balance between how much tissue is being destroyed and how much is being formed. The protein fragments released when tissue breaks down give us the most direct way to measure that balance. 

    By bringing together perspectives on biomarkers, synovial pathobiology, and fibrogenesis, this webinar examines how measuring tissue activity—not only inflammation—could improve patient characterization, pharmacodynamic assessment, and ultimately drug development in rheumatology.

    Speakers

    Dr. Kevin Wei

    • Dr. Kevin Wei is an Assistant Professor of Medicine at Harvard Medical School and a rheumatologist at Brigham and Women’s Hospital. 
    • His research focuses on identifying novel cellular and molecular therapeutic targets in inflammatory diseases using single-cell technologies. 
    • Dr. Wei is a member of the NIH Accelerating Medicines Partnership in Rheumatoid Arthritis and Systemic Lupus Erythematosus (AMP-RA/SLE) consortium. 
    • Within the consortium, he leads the implementation of single-cell technologies to study rheumatoid arthritis joint tissues. 
    • He is Co-Director of the Brigham and Women’s Hospital Center for Cell Profiling Single Cell Multiomics Core. 
    • Dr. Wei also serves as Associate Director of the Harvard Medical School/BWH Joint Biology Consortium Cellular Systems Core. 
    • His work applies advanced cellular profiling and multiomics approaches to better understand disease mechanisms and tissue-specific cellular states in rheumatic diseases. 
    • He has received research awards from the Rheumatology Research Foundation, Burroughs Wellcome Fund, Harvard Catalyst, and the BWH Department of Medicine. 
    • Dr. Wei earned his BS in Biology from Duke University and his MD and PhD from Stanford University School of Medicine. 
    • He completed his Internal Medicine residency and Rheumatology fellowship at Brigham and Women’s Hospital and also serves on the advisory board of STAR Protocols. 

    Prof. Dr. Morten Karsdal

    • Dr. Morten Karsdal joined Nordic Bioscience in 2001 and became CEO in June 2010, leading the company to significant advancements in biomarker development and disease biology.
    • Dr. Karsdal is a KOL in extracellular matrix research, with more than 700 publication, 44,684 citations, and an impressive H-index of 106.
    • Dr. Karsdal is an honorary professor of inflammation research at the University of Southern Denmark, where he continues to supervise PhD students, fostering the next generation of researchers.
    • Dr. Karsdal chairs the Extracellular Matrix Pharmacology Congress, an important forum for advancing drug development by focusing on the extracellular matrix (ECM) as a key factor in most chronic diseases. He is renowned for his deep expertise in fibrosis, rheumatology (including rheumatoid arthritis and osteoarthritis), diabetes, and other chronic conditions, particularly in relation to ECM and biomarker research.
    • Dr. Karsdal has led the development of FDA-approved and supported molecular diagnostics, as well as more than 100 commercialized biomarker assays, including ELISA assays and high precision automated platforms.
    • He has extensive experience in clinical trial design and the clinical application of biochemical markers, often serving as a consultant to major pharmaceutical companies for the use of serological biomarkers in clinical trials.
    • In 2016, he and his research team authored the first edition of “Biochemistry of Collagens, Laminins and Elastin,” published by Elsevier Science. The book, now in its 3rd edition as of 2023, is a key resource on collagens and structural proteins, with a focus on their applications in chronic diseases.

    Prof. Dr. Shervin Assassi

    • Dr. Shervin Assassi is Professor of Medicine and Director of the Division of Rheumatology at UTHealth Houston’s McGovern Medical School. 
    • He is Co-Director of the Scleroderma Program, which includes one of the largest specialized scleroderma clinics in the United States. 
    • His research focuses on systemic sclerosis (scleroderma), integrating clinical features with genetic and gene-expression data to better understand disease mechanisms. 
    • Dr. Assassi’s laboratory aims to identify novel therapeutic targets and clinically useful biomarkers for systemic sclerosis. 
    • His translational research combines primary human samples with experimental models of fibrosis to investigate the molecular mechanisms underlying the disease. 
    • He is a leader of the Scleroderma Research Foundation-funded CONQUER Registry, serving as Chair of its Executive Committee and Director of the CONQUER Biorepository. 
    • Dr. Assassi has co-authored more than 220 peer-reviewed publications in systemic sclerosis, fibrosis, biomarkers, and related areas. 
    • His research program is supported by the National Institutes of Health, the Scleroderma Research Foundation, and industry collaborations. 
    • He holds a Master’s degree in Clinical Research and additional academic appointments in biomedical informatics and biomedical sciences. 
    • Alongside his research and clinical leadership, Dr. Assassi contributes to translational research education and holds leadership positions in professional rheumatology organizations and multicenter research consortia. 

    Dr. Anne-Christine Bay-Jensen 

    • Dr. Anne-Christine Bay-Jensen is Chief Technology Officer (CTO) and Director of Immunoscience at Nordic Bioscience, where she has worked since 2008. 
    • She joined Nordic Bioscience as a postdoctoral researcher and has since progressed into senior scientific and technology leadership roles. 
    • Her research focuses on the development of novel biomarkers for rheumatic and immune-mediated diseases, with approximately two decades of experience in the field. 
    • Dr. Bay-Jensen’s work uses biomarkers to characterize disease activity, tissue remodeling, and treatment response, supporting the development of precision medicine approaches. 
    • Her research has a strong focus on osteoarthritis and rheumatoid arthritis, including disease mechanisms, patient stratification, and therapeutic evaluation. 
    • Her scientific work also spans spondyloarthritis, systemic sclerosis, inflammatory bowel disease, inflammatory mediators, pharmacology, and immunology. 
    • A central theme of her research is understanding how changes in tissues and the extracellular matrix (ECM) can provide measurable insights into chronic inflammatory and connective tissue diseases. 
    • As CTO, she combines scientific leadership with the development and translation of biomarker technologies for use in preclinical research and clinical drug development. 
    • Dr. Bay-Jensen has an h-index of 66, i10-index of 229, and more than 13,600 citations as of September 2026. 
    • Her work bridges biomarker discovery, disease biology, and clinical translation to improve the characterization and treatment of rheumatic and inflammatory diseases. 

    This webinar was co-hosted with the International Society of Extracellular Matrix Pharmacology.

    PRO-C11 is associated with disease activity and treatment response in patients with HS

    The fibroblast activity biomarkers, PRO-C11, quantified in serum, is associated with disease activity and treatment response in patients with hidradenitis suppurativa

    Introduction

    Hidradenitis suppurativa (HS) is a chronic inflammatory skin disease characterized by inflammatory nodules, abscesses and sinus tracts. A key pathological feature is fibrosis, which is caused by accumulation of extracellular matrix (ECM) proteins. Type XI collagen is a minor fibrillar collagen, produced by dermal fibroblasts, and are upregulated in skin fibrosis. This study investigated the relationship between the serological biomarker PRO-C11, quantifying type XI  collagen formation, with disease severity and treatment response in HS patients.

    Poster

    Conclusion

    The serum biomarker PRO-C11 was associated with disease severity in patients with HS, and mildly associated with IHS 4 improvement after 3-6 months of anti TNF α treatment. Such biomarker may serve as objective measures of fibrosis and tissue remodeling in HS, help identifying patients at risk of disease progression and the evaluation of treatment response.

    Get in touch

    Are you interested in exploring collaboration possibilities?
Enter your information in the form and a representative will contact you shortly.

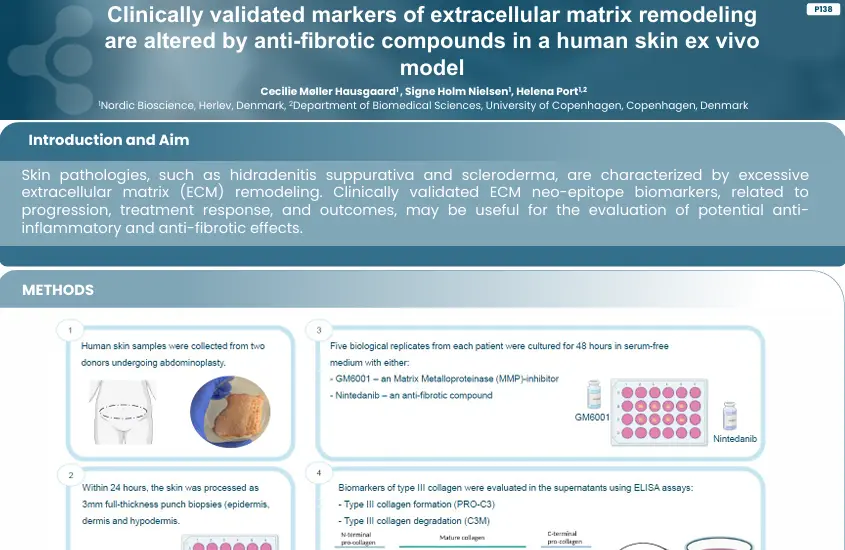
      ECM remodeling markers are altered by anti-fibrotic compounds in human skin ex vivo model

      Clinically validated markers of extracellular matrix remodeling are altered by anti-fibrotic compounds in a human skin ex vivo model

      Introduction

      Skin pathologies, such as hidradenitis suppurativa and scleroderma, are characterized by excessive extracellular matrix (ECM) remodeling. Clinically validated ECM neo-epitope biomarkers, related to progression, treatment response, and outcomes, may be useful for the evaluation of potential anti-inflammatory and anti-fibrotic effects.

      Poster

      Conclusion

      This study found that an MMP-inhibitor and anti-fibrotic decreased biomarkers of ECM remodeling in a human skin ex vivo model and may potentially be used as a tool for evaluating anti-inflammatory and anti-fibrotic compounds in a 3D skin structure.

      Get in touch

      Are you interested in exploring collaboration possibilities?
Enter your information in the form and a representative will contact you shortly.

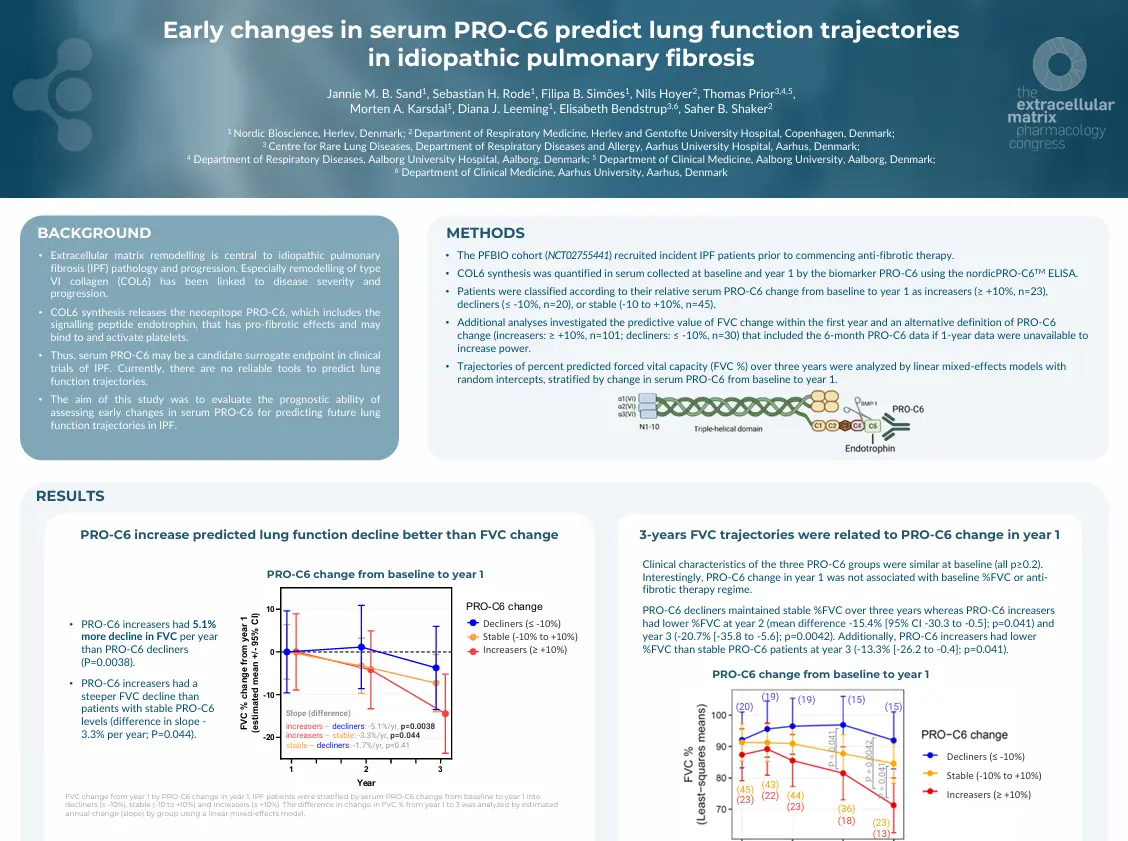
        Early changes in serum PRO-C6 predict lung function trajectories in IPF

        Early changes in serum PRO-C6 predict lung function trajectories in idiopathic pulmonary fibrosis

        Introduction

        Extracellular matrix remodeling is central to idiopathic pulmonary fibrosis (IPF) pathology and progression. Especially remodeling of type VI collagen (COL6) has been linked to disease severity and progression. COL6 synthesis releases the neoepitope PRO-C6, which includes the signaling peptide endotrophin, that has pro-fibrotic effects and may bind to and activate platelets. Thus, serum PRO-C6 may be a candidate surrogate endpoint in clinical trials of IPF. Currently, there are no reliable tools to predict lung function trajectories.

        The aim of this study was to evaluate the prognostic ability of assessing early changes in serum PRO-C6 for predicting future lung function trajectories in IPF.

        Poster

        Conclusion

        This study found that increases in serum PRO-C6 were prognostic for future FVC decline, suggesting that PRO-C6 dynamics may identify high risk patients and could be a surrogate endpoint in clinical trials and a tool to improve patient care.

        Get in touch

        Are you interested in exploring collaboration possibilities?
Enter your information in the form and a representative will contact you shortly.

          Biomarkers of collagen turnover and immune cell activity distinguish fibrotic HP from IPF

          Biomarkers of collagen turnover and immune cell activity distinguish fibrotic hypersensitivity pneumonitis from idiopathic pulmonary fibrosis

          Introduction

          Idiopathic pulmonary fibrosis (IPF) is the most common cause of pulmonary fibrosis (PF), although it is also present in other interstitial lung diseases (ILDs). This includes hypersensitivity pneumonitis (HP), which is an inflammatory disease caused by an exacerbated response to environmental antigens and can be classified into fibrotic (fHP) or non-fibrotic (non-fHP). Due to the various differences between IPF and fHP, tools to aid the distinction are needed.

          This study aimed to assess tissue remodeling and immune cell activity biomarkers as potential tools to distinguish between HP phenotypes and IPF.

          Poster

          Conclusion

          The findings of this study are reflective of the different pathophysiological characteristics underlying each disease and highlights the potential of non-invasive serological biomarkers collagen and immune cell activity as potential tools to distinguish between HP and IPF in the clinic.

          Get in touch

          Are you interested in exploring collaboration possibilities?
Enter your information in the form and a representative will contact you shortly.

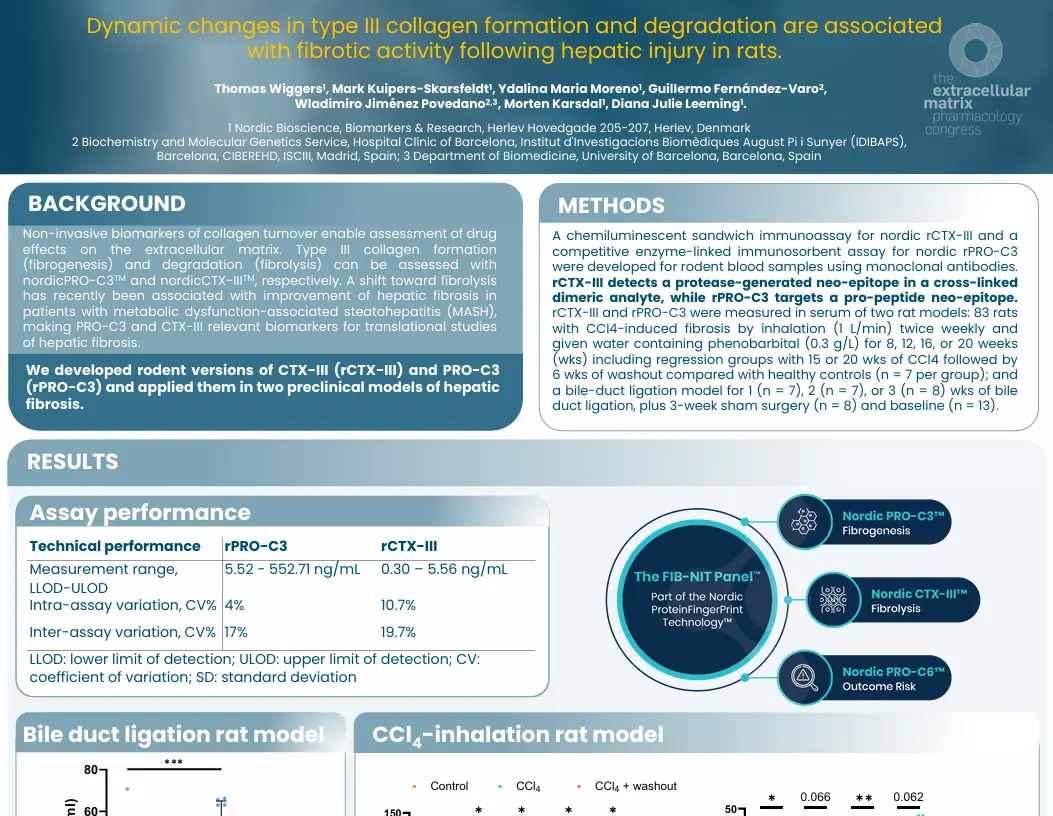
            Type III collagen turnover is associated with fibrotic activity following hepatic injury in rats

            Dynamic changes in type III collagen formation and degradation are associated with fibrotic activity following hepatic injury in rats

            Introduction

            Non-invasive biomarkers of collagen turnover enable assessment of drug effects on the extracellular matrix. Type III collagen formation (fibrogenesis) and degradation (fibrolysis) can be measured with
            nordicPRO-C3™ and nordicCTX-III™, respectively. A shift toward fibrolysis has recently been associated with improvement of hepatic fibrosis in patients with metabolic dysfunction-associated steatohepatitis (MASH), making PRO-C3 and CTX-III relevant biomarkers for translational studies of hepatic fibrosis.
            I this study, rodent versions of CTX-III (rCTX-III) and PRO-C3 (rPRO-C3) were developed and applied in two preclinical models of hepatic fibrosis.

            Poster

            Conclusion

            In this study we developed robust assays for the rodent fibrolysis biomarker rCTX-III and fibrogenesis biomarker rPRO-C3. The biomarkers were applied in two hepatic fibrosis rat models, showing increased
            type III collagen turnover after injury. In conclusion, rCTX-III and rPRO-C3 may serve as translational biomarkers in antifibrotic drug development.

            Get in touch

            Are you interested in exploring collaboration possibilities?
Enter your information in the form and a representative will contact you shortly.

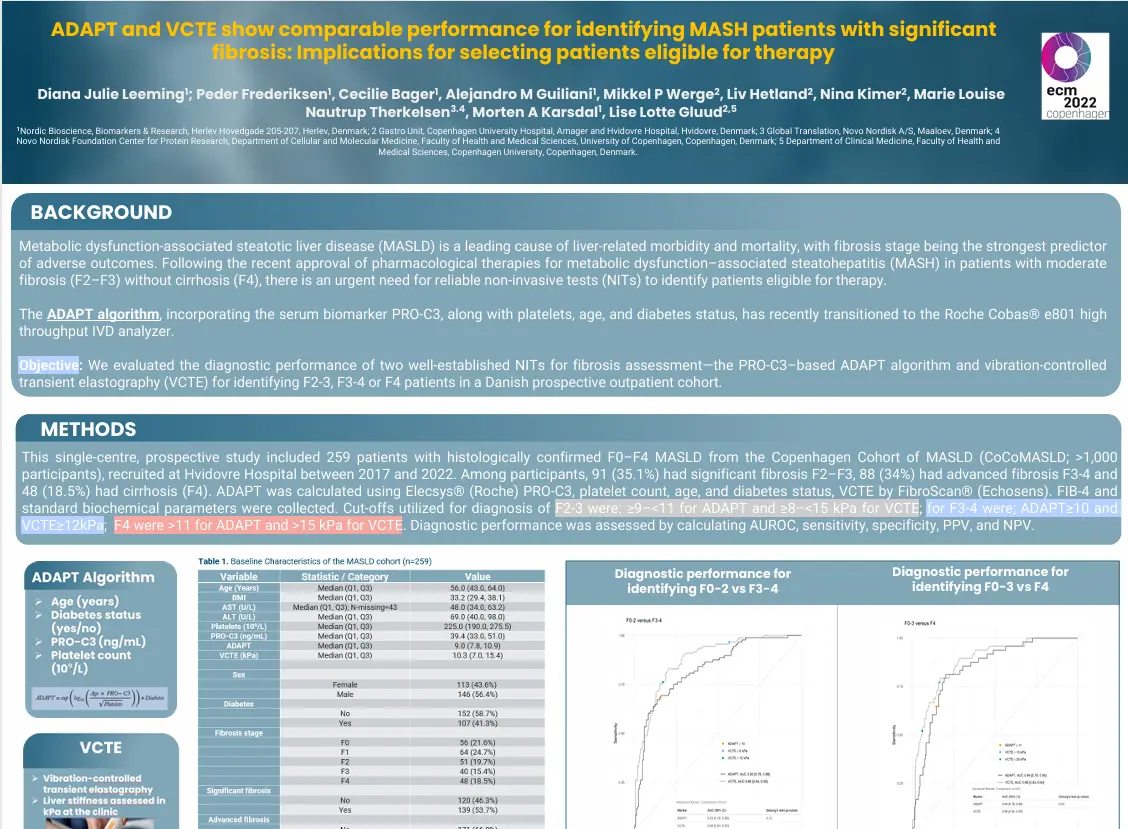
              ADAPT and VCTE show comparable performance for identifying MASH patients with significant fibrosis

              ADAPT and VCTE show comparable performance for identifying MASH patients with significant fibrosis: Implications for selecting patients eligible for therapy

              Introduction

              Metabolic dysfunction-associated steatotic liver disease (MASLD) is a leading cause of liver-related morbidity and mortality, with fibrosis stage being the strongest predictor of adverse outcomes. Following the recent approval of pharmacological therapies for metabolic dysfunction–associated steatohepatitis (MASH) in patients with moderate fibrosis (F2–F3) without cirrhosis (F4), there is an urgent need for reliable non-invasive tests (NITs) to identify patients eligible for therapy. The ADAPT algorithm, incorporating the serum biomarker PRO-C3, along with platelets, age, and diabetes status, has recently transitioned to the Roche Cobas® e801 high throughout IVD analyzer.

              This study evaluated the diagnostic performance of two well-established NITs for fibrosis assessment – the PRO-C3-based ADAPT algorithm and vibration-controlled transient elastography (VCTE) for identifying F2-3, F3-4 or F4 patients in a Danish prospective outpatient cohort.

              Poster

              Conclusion

              ADAPT and VCTE performed similarly in detecting F2-F3, F3-4 fibrosis or F4 cirrhosis, one being blood-based and the other imaging-based. As many F2-F3 cases are missed, this indicates a large number of patients may be left untreated using only one text. These findings support further investigating of NITs for non-invasive fibrosis assessment and for identifying patients eligible for MASH therapy.

              Get in touch

              Are you interested in exploring collaboration possibilities?
Enter your information in the form and a representative will contact you shortly.

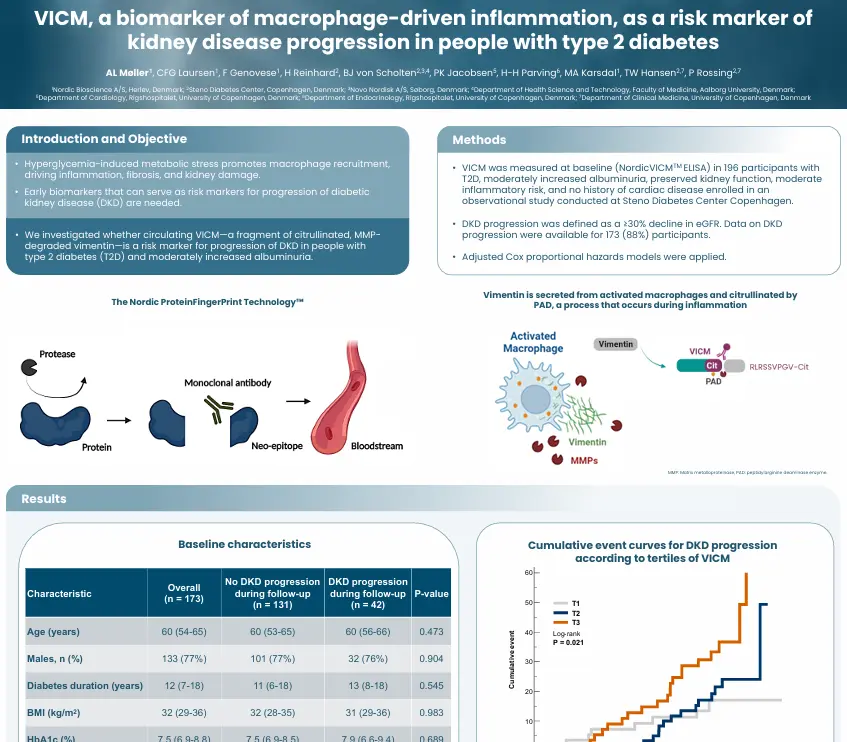
                VICM as a risk marker of kidney disease progression in people with type 2 diabetes

                VICM, a biomarker of macrophage-driven inflammation, as a risk marker of kidney disease progression in people with type 2 diabetes

                Introduction

                Hyperglycemia-induced metabolic stress promotes macrophage recruitment, driving inflammation, fibrosis, and kidney damage. Early biomarkers that can serve as risk markers for progression of diabetic kidney disease (DKD) are needed. We investigated whether circulating VICM—a fragment of citrullinated, MMP-degraded vimentin—is a risk marker for progression of DKD in people with type 2 diabetes (T2D) and moderately increased albuminuria.

                Poster

                Conclusion

                Higher VICM is an independent risk marker of DKD progression in people with T2D. Biomarkers reflecting macrophage-driven immune dysregulation, such as VICM, may enable early identification of people at high risk of kidney complications.

                Get in touch

                Are you interested in exploring collaboration possibilities?
Enter your information in the form and a representative will contact you shortly.